
🫁 When TB Becomes Hard to Treat
 ToothOps3 min read

The Quiet Biology Behind Tuberculosis Drug Resistance
Most people think drug resistance happens when antibiotics are “used wrong.”
Tuberculosis is different.
TB doesn’t become drug-resistant because treatment exists —it becomes drug-resistant because survival makes resistance statistically inevitable.
This post explains why — calmly, clearly, and without fear.
🎯 Clinical Reasoning
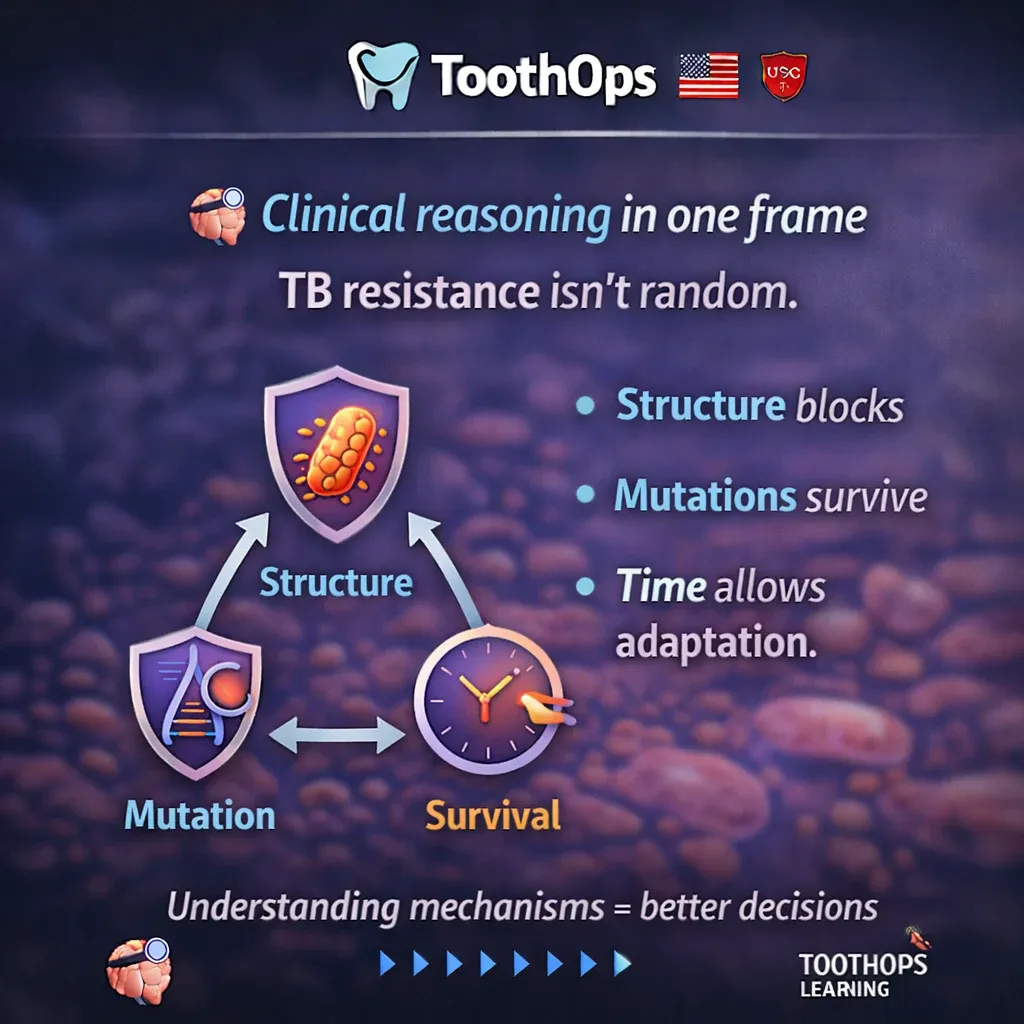
Drug-resistant TB isn’t a mistake.It’s the predictable outcome of structure, mutation, and survival.
1️⃣ What Drug-Resistant TB Really Means (Beyond the Labels)
Drug-resistant TB is classified by which antibiotics no longer work:
- RR-TB → rifampicin resistant
- MDR-TB → resistant to isoniazid + rifampicin
- Pre-XDR TB → MDR + fluoroquinolone resistance
- XDR-TB → MDR + fluoroquinolone + key reserve drugs
As resistance accumulates:
- Treatment duration increases
- Toxicity rises
- Outcomes worsen
📌 But classification tells you what failed — not why.

2️⃣ Why TB Is Different From Most Bacteria
🧠 Analogy Box
If most bacteria wear a jacket, TB wears a waxed raincoat and lives in a bunker.
TB’s cell wall is:
- Lipid-rich
- Hydrophobic
- Reinforced with mycolic acids
- Poorly permeable to many antibiotics
Mechanism → consequence → relevance
- Mechanism: Thick, waxy barrier
- Consequence: Low intracellular drug levels
- Relevance: TB survives exposure that would kill other bacteria
This is intrinsic resistance — present before mutations occur.
3️⃣ The Most Important Insight (Most Students Miss This)
TB resistance often exists before treatment begins.
Why?
Because TB resistance arises from spontaneous chromosomal mutations, not gene sharing.
The more bacteria present:
- The higher the chance mutations already exist
- The more likely treatment selects resistant subpopulations
📌 High bacterial burden = higher resistance risk.
This is why:
- Cavitary disease matters
- Early combination therapy matters
- Partial treatment is dangerous biologically — not morally

4️⃣ The Three Layers of TB Drug Resistance (Think in Systems)
🧩 Layer 1: Physical barriers
- Waxy cell wall
- Poor penetration
🧩 Layer 2: Genetic mutations
- rpoB → rifampicin
- katG / inhA → isoniazid
- gyrA / gyrB → fluoroquinolones
These alter targets or block prodrug activation.
🧩 Layer 3: Metabolic state
- Dormant or slow-growing bacteria
- Reduced susceptibility to many drugs
💡 Resistance isn’t one trick — it’s a stacked defense.
5️⃣ Efflux Pumps: Time Is the Enemy
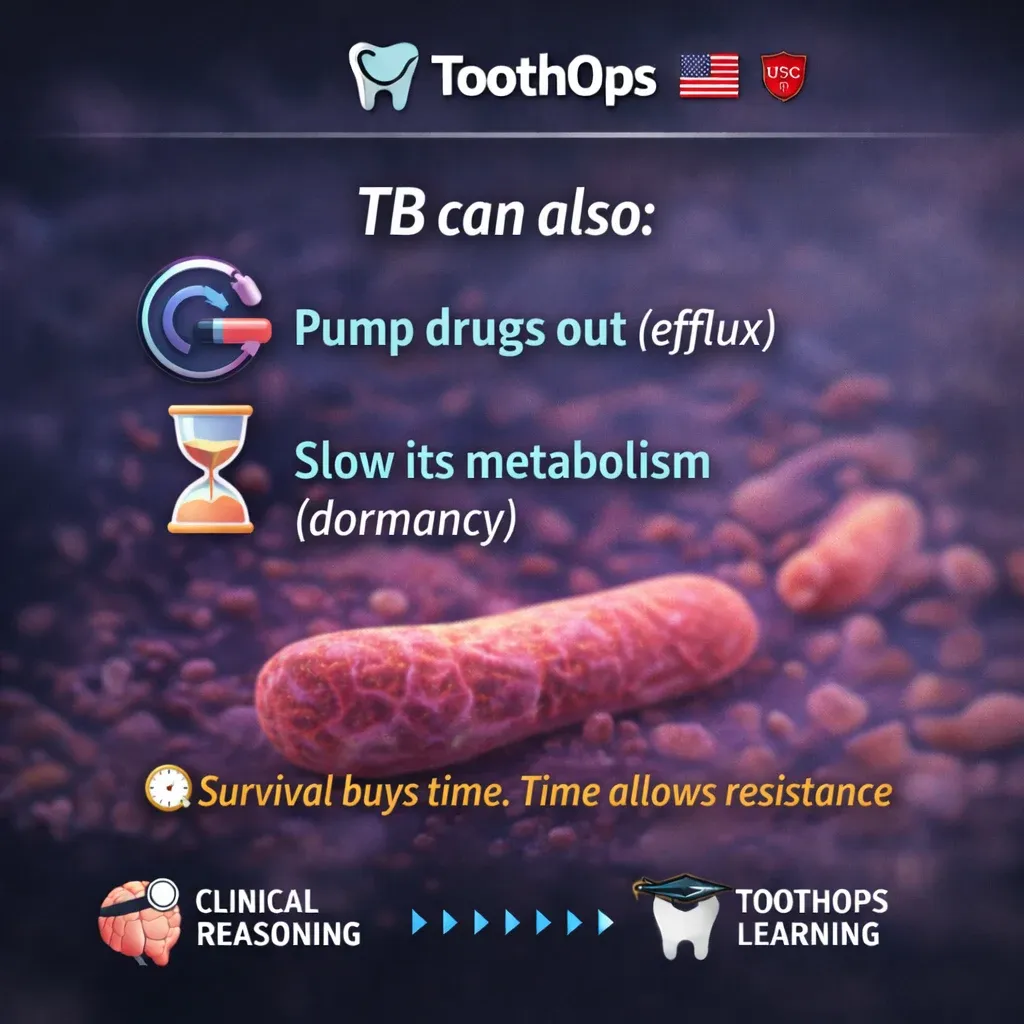
TB also uses efflux pumps to push drugs out.
Efflux alone may not cause resistance — but it:
- Buys time
- Lowers effective drug concentration
- Allows mutations to accumulate
🧠 Efflux turns survival into opportunity.
📊 Clinical Reasoning Snapshot
| Resistance Factor | What It Does | Why It Matters |
|---|---|---|
| Waxy cell wall | Limits entry | Intrinsic tolerance |
| Point mutations | Alter targets | True resistance |
| Efflux pumps | Expel drugs | Mutation window |
| Dormancy | Low metabolism | Drug tolerance |
| Cavitation | Poor penetration | Selection pressure |
6️⃣ Why Multidrug Therapy Works (And Monotherapy Fails)
No single drug can overcome:
- Barriers
- Mutations
- Dormancy
- Efflux
Combination therapy works because it:
- Hits multiple pathways
- Targets active + inactive populations
- Prevents one mutation from guaranteeing survival
💡 This is why isoniazid is never given alone.
7️⃣ Adherence Is Biology, Not Blame
Missed doses don’t “create” resistance.They select organisms already capable of surviving.
Directly observed therapy matters because it:
- Prevents subtherapeutic exposure
- Reduces selective pressure
- Protects future treatment options
This is evolutionary math, not personal failure.
8️⃣ Where TB Treatment Is Heading
Modern strategies now include:
- Host-directed therapy
- Drug repurposing (e.g., metformin, statins)
- Improved drug delivery systems
- Targeting bacterial persistence mechanisms
The goal isn’t just killing TB —it’s preventing survival long enough to adapt.
🌱 Final ToothOps Takeaway
Drug-resistant TB isn’t mysterious.It’s the outcome of structure, survival, and selection.
When you understand that, treatment stops feeling arbitrary —and clinical reasoning becomes calm, confident, and precise.
@ToothOps | Fuel Your Smile 😊Stay tuned for more insights and educational content in our blog.
Disclaimer: Content is for educational purposes only and not a substitute for medical or dental care.
© 2025 ToothOps | All Rights Reserved.