
🦠 IMMUNE RESPONSE TO FUNGAL INFECTIONS
 ToothOps5 min read

A ToothOps Guide for Dental Students, Pre-Dentals & Curious Minds
Fungal infections are one of the most fascinating — and misunderstood — topics in immunology. Unlike bacteria and viruses, fungi are eukaryotes with unique cell walls and slow replication cycles. Most of the time, our bodies win easily. But when immunity drops, fungi take the opportunity to invade.
This guide breaks down exactly how the immune system fights fungi, with a special focus on the oral cavity, granulomas, and the innate vs. adaptive responses — in a way that’s exam-friendly, clinically relevant, and easy to remember.
Let’s dive in.
⭐ 1. Why Humans Are Naturally Resistant to Fungi
Most people with normal immunity rarely develop serious fungal infections because:
- Neutrophils and macrophages rapidly kill most fungal spores
- Our intact skin and mucosa act as strong physical barriers
- Saliva contains antifungal proteins (histatins, lysozyme, lactoferrin)
- The immune system can form granulomas when fungi survive inside macrophages
Still, in the right conditions — immunosuppression, xerostomia, antibiotic use, diabetes — fungi can shift from harmless colonizers to invasive pathogens.
⭐ 2. Candida albicans — The Opportunist Among Us
- Candida albicans lives in the oral cavity, GI tract, and vagina as part of the normal flora.
- In healthy hosts, it stays controlled.
- In immunocompromised or dry-mouth environments, it overgrows and switches from yeast → hyphal form — increasing invasion and virulence.
What triggers overgrowth?
- Xerostomia
- Diabetes
- Dentures (especially uncleaned)
- Broad-spectrum antibiotics
- Inhaled corticosteroids
- High carbohydrate diets
Clinical forms in dentistry:
- Pseudomembranous candidiasis (“thrush”)
- Erythematous candidiasis
- Denture stomatitis
- Angular cheilitis
⭐ 3. Granulomas in Fungal Infections
Many systemic fungal infections produce granulomas, including:
- Histoplasmosis
- Coccidioidomycosis
- Blastomycosis
- Cryptococcosis
Granulomas form when fungi cannot be fully eliminated, prompting the immune system to wall them off.
Key pathway:
- Dendritic cells + macrophages present antigen
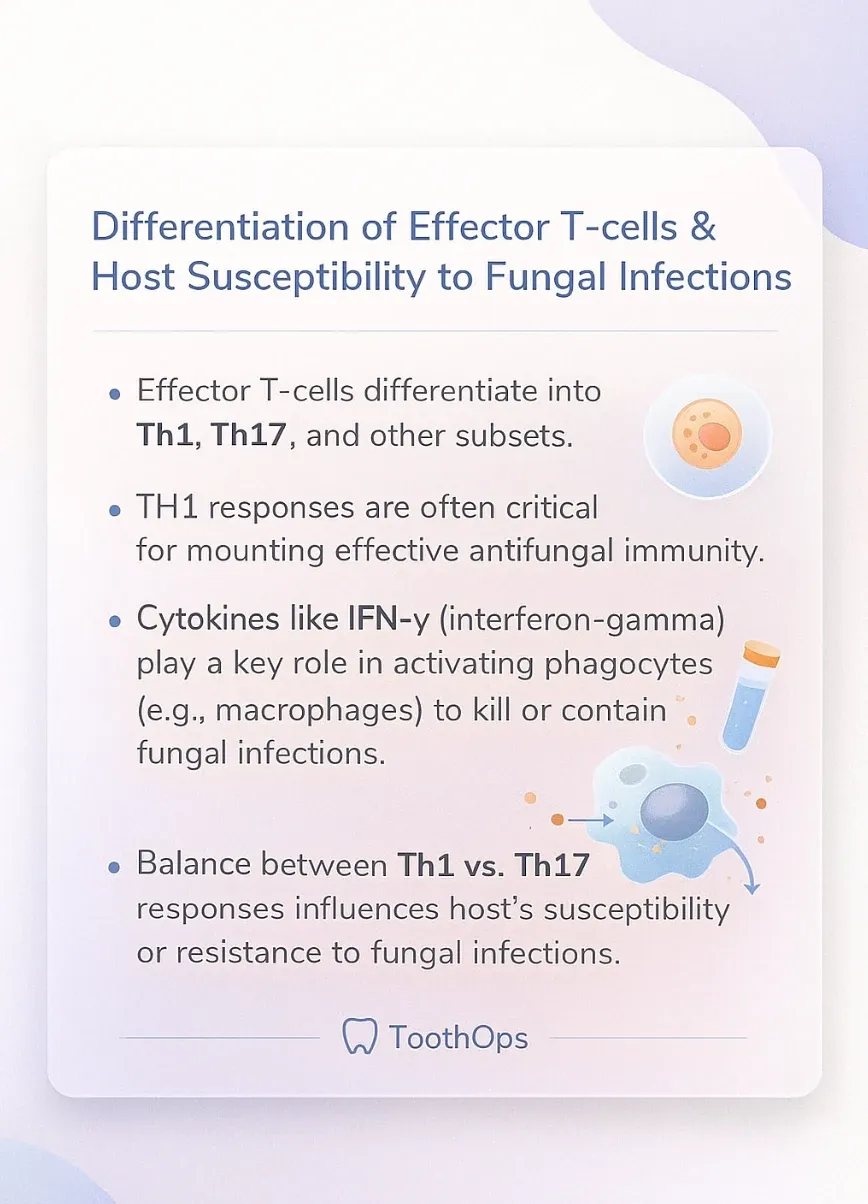
- CD4+ T-cells → differentiate into Th1 cells
- Th1 cells release IFN-γ
- Macrophages activate, transform into epithelioid cells
- Some fuse into multinucleated giant cells
- Fibroblasts lay collagen → forming a structured granuloma
🧠 Clinical pearl: Caseating granulomas often suggest TB or fungal infections, while non-caseating granulomas (no necrosis) are common in sarcoidosis.
⭐ 4. First Line of Defense: Skin, Mucosa & Saliva
Skin & epithelial barriers
- Healthy skin stops dermatophytes and opportunistic fungi.
- Damaged or macerated skin → fungal invasion becomes possible.
Respiratory & mucosal defenses
- Nasopharyngeal mucosa traps and filters spores.
- Alveolar macrophages engulf most inhaled fungi before infection occurs.
Humoral immunity:
- Systemic fungal infections trigger production of IgG and IgM, aiding opsonization.
- But antibodies alone rarely clear fungi — cell-mediated immunity is the true hero.
⭐ 5. Fungal Immune Evasion Strategies
Pathogenic fungi have evolved ways to survive our immune system, such as:
- Antioxidant enzymes to neutralize ROS
- Cell wall masking (hiding β-glucans from PRRs like Dectin-1)
- Thick capsules (Cryptococcus) to prevent phagocytosis
- Dimorphic switching (yeast ↔ mold)
- Biofilm formation — critical for Candida on dentures, implants, and mucosa
These survival strategies explain why fungal infections are often chronic and sometimes recurrent.
⭐ 6. Immune Response Process (Innate → Adaptive)
Innate response: Rapid, nonspecific
- Neutrophils are the primary killers of fungi
- Use oxidative burst, NETs, and antimicrobial peptides
- Macrophages engulf spores, release cytokines, and activate T-cells
- Dendritic cells capture fungal antigens and migrate to lymph nodes
- NK cells release perforin and granzyme against infected host cells
Key cytokines + signals:
- IL-1, IL-6, TNF-α → inflammation
- IL-12 → drives Th1 differentiation
- IL-17 → crucial for mucosal candidiasis defense (Th17 pathway)
⭐ 7. Adaptive Immunity Against Fungi
Th1 Response (Most important for systemic fungi)
- IFN-γ activates macrophages
- Critical for Histoplasma, Blastomyces, Coccidioides
Th17 Response (Critical for oral & mucosal fungi)
- IL-17 & IL-22 recruit neutrophils and stimulate epithelial antimicrobial peptides
- Plays a central role in preventing oral candidiasis
Antibodies:
- IgG and IgM aid opsonization, but fungi are often resistant to antibody-mediated killing.
- IgA dominates the oral cavity, preventing adherence and biofilm formation.
⭐ 8. Antifungal Drugs — How They Work
Antifungal medications target structures unique to fungal cells, such as:
- Ergosterol (instead of cholesterol)
- Polyenes bind it (amphotericin B)
- Azoles inhibit its synthesis
- Allylamines (terbinafine) block squalene epoxidase
- β-glucan in fungal cell walls
- Echinocandins inhibit β-glucan synthase
These unique pathways allow us to treat fungi without harming human cells (at least in theory — amphotericin B nephrotoxicity still says hello).
⭐ 9. Oral Fungal Infections: Innate Defense
(High yield for dentistry)
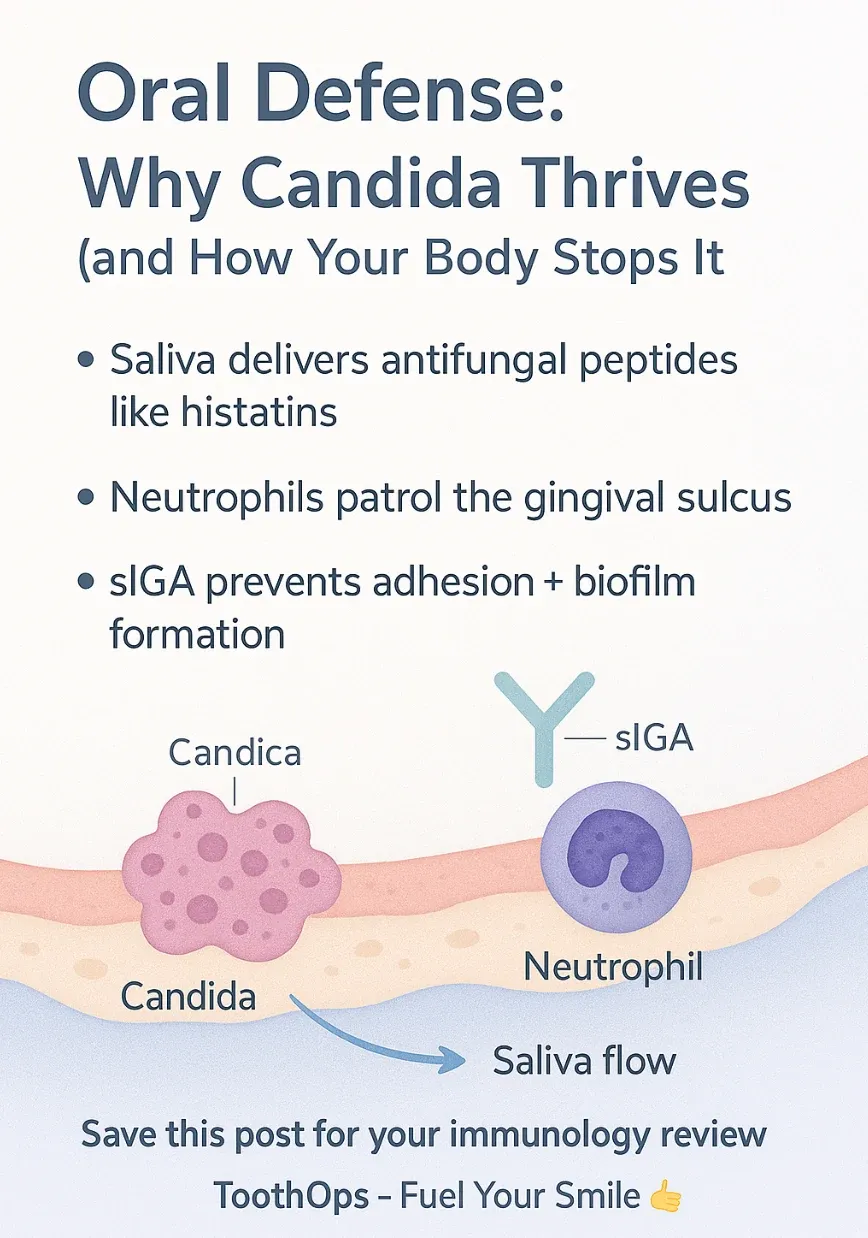
Oral innate defenses include:
- Salivary flow
- Antimicrobial peptides such as histatins, which specifically damage Candida
- Neutrophils patrolling the gingival crevice
- Normal oral microbiota competing with fungal colonizers
- Mechanical cleansing from mastication and swallowing
Macrophages survive longer than neutrophils, helping maintain chronic surveillance in mucosa.
⭐ 10. Oral Fungal Infections: Adaptive Defense
- Adaptive responses include humoral (IgA) and cell-mediated immunity.
- In the oral cavity, the most important immunoglobulin is secretory IgA (sIgA), which:
- Agglutinates Candida
- Blocks adhesion to epithelial surfaces
- Helps maintain healthy microbial balance
Th17 responses are especially important — patients with IL-17 deficiencies often develop chronic mucocutaneous candidiasis.
⭐ 11. ToothOps Clinical Takeaways for Dentistry
You will see fungal infections often. Look for:
- Red or white patches that scrape off
- Glossy red tongue (erythematous candidiasis)
- Denture-associated erythema
- Angular cheilitis
- Burning sensation with no visible lesions (early infection)
Patients at increased risk:
- Diabetics
- Xerostomia patients (radiation, medications, Sjögren’s)
- Denture wearers
- Immunocompromised individuals
- Asthma/COPD patients using steroid inhalers
What you can do as a dental provider:
- Encourage denture hygiene + overnight removal
- Recommend rinsing after steroid inhaler use
- Evaluate for systemic contributors (diabetes, hyposalivation, meds)
- Prescribe antifungals appropriately (nystatin, clotrimazole, fluconazole)
- Educate patients on prevention and recurrence management