
🦷 White Spot vs Cavity: How Dentists Know When to Drill — and When NOT To.
 ToothOps4 min read
You’re brushing your teeth one night and suddenly notice a tiny chalky patch near your gumline. Cue the panic:
“Oh no… is that a cavity?”“Do I need a filling?”“Is this going to hurt??”
⭐ A white spot does NOT automatically mean “drill.”
⭐ Many of these early spots can be reversed.
⭐ The difference between “needs treatment” and “needs monitoring” is all about activity.
Let’s break down how dentists actually make that call — and why it’s a lot more scientific than you think.
1️⃣ What Is a White Spot Lesion?
A white spot lesion is the earliest visible sign of enamel demineralization, caused by acid dissolving minerals from the surface.
But here’s the KEY:
🔹 There are active white spots
🔹 There are inactive white spots
And they behave completely differently.
🧠 Analogy: Think of enamel like a sidewalk.An active lesion is like wet cement — still soft, still changing, still at risk.An inactive lesion is like dried cement — the mark is there, but it’s stable.
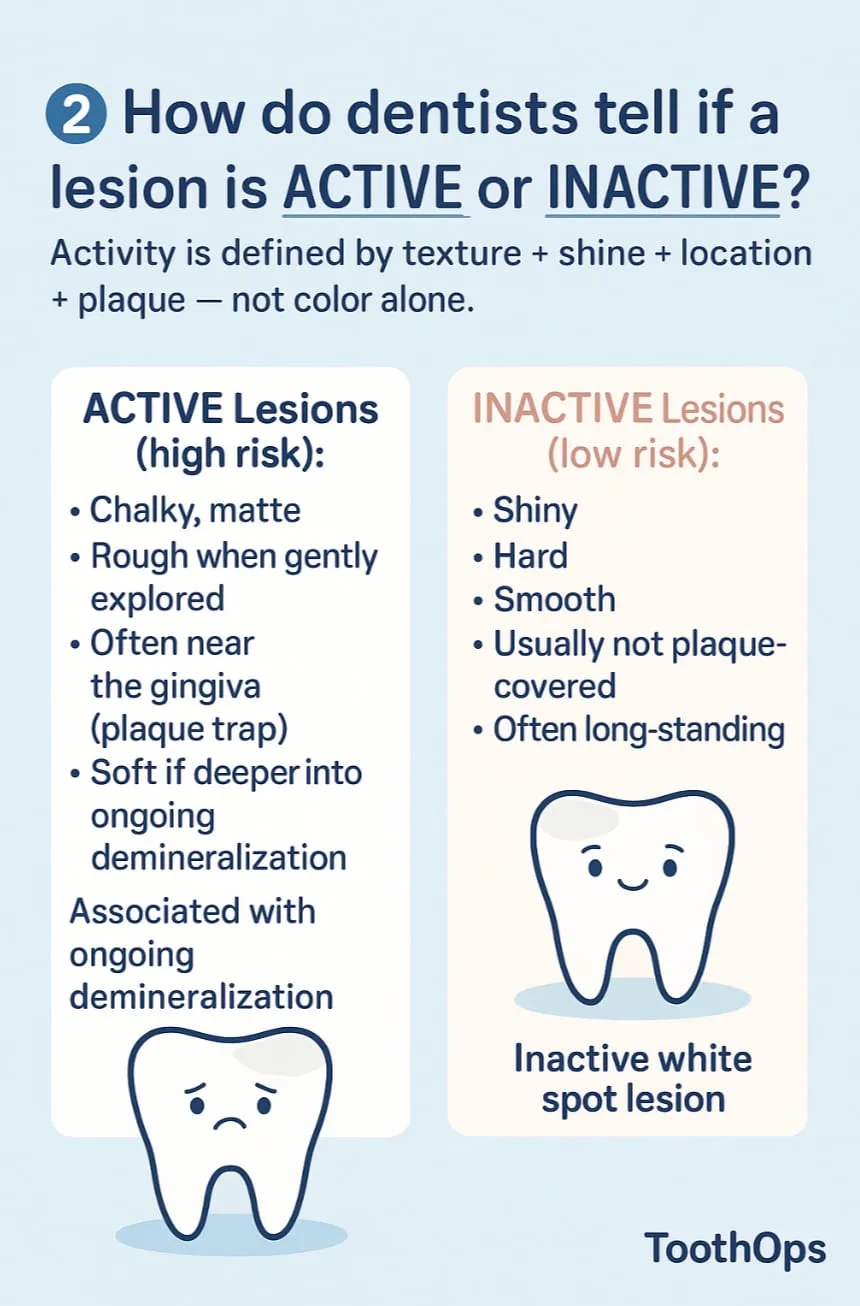
2️⃣ How Dentists Tell If a Lesion Is Active or Inactive
Activity is defined by texture + shine + location + plaque — not color alone.
ACTIVE Lesions (high risk):
- Chalky, matte
- Rough when gently explored
- Often near the gingiva (plaque trap)
- Soft if deeper into dentin
- Associated with ongoing demineralization
👉 These CAN often be reversed with fluoride, sealants, improved hygiene, reduced sugar frequency, and risk management.
INACTIVE Lesions (low risk):
- Shiny
- Hard
- Smooth
- Usually not plaque-covered
- Often long-standing
👉 **These do NOT need drilling.**They’re essentially scars from past disease that has already arrested.
🧠 **Pearl for dental students:**The #1 mistake beginners make is “treating color instead of activity.”
3️⃣ Radiographs & Depth: Why ICDAS Matters
Dentists don’t simply eyeball a spot and decide.Radiographs help us determine how far the lesion has progressed.
- E1 → outer half of enamel
- E2 → inner half of enamel
- D1 → outer dentin
- D2 → middle dentin
- D3 → deep dentin
How this guides treatment:
- E1 / E2 → reversible in many cases
- D1 → may still be treated non-operatively if non-cavitated & low risk
- D2 / D3 → restorative treatment usually needed
🧠 **Analogy:**Enamel is like a castle wall.If erosion is on the outer bricks (E1/E2), we can rebuild. If it reaches the foundation (D2/D3), the structure needs reinforcement (filling).
4️⃣ Modern Dentistry: Why “Drill = Last Resort”
Old-school mentality:“Dark spot? Fill it.”
Modern evidence-based practice:“Caries is a disease. The cavity is a symptom.”
fThe medical model of caries:
✔ Control the disease first
✔ Strengthen protective factors
✔ Fix the tooth only when necessary
Non-drill options include:
- Fluoride varnish
- High-fluoride toothpaste or gels
- Remineralizing products (calcium phosphate, arginine-based, etc.)
- Xylitol
- Sealants on pits/fissures
- Dietary modifications
- CAMBRA risk management
- Dry mouth interventions
🧠 **Key insight:**A filling does NOT cure caries — it only repairs the damage.
5️⃣ When Dentists Do Recommend a Filling
There ARE times drilling is absolutely the right call.
Dentists intervene when:
✔ The lesion is cavitated (a hole is present)
✔ The enamel surface is broken
✔ Radiographs show clear dentin involvement (D2/D3)
✔ The patient is high risk AND the lesion is progressing
✔ The patient cannot maintain plaque control
In those cases, a restoration prevents the lesion from spreading, protects pulpal health, and restores function.

6️⃣ Why This Matters for Students, Pre-Dentals, and Patients
For Dental Students:
Understanding activity vs depth is a core part of:
- OSCEs
- PBL cases
- Essentials exams
- Clinic grading
- Patient-centered care
For Pre-Dentals:
Talking about diagnosis in this way sets you apart instantly.It shows you understand dentistry as preventive medicine, not just drilling.
For Patients:
You gain clarity.You learn why your dentist might choose:
- “Monitor this.”
- “Let’s remineralize this first.”
- “We don’t need a filling yet.”
- OR “This needs treatment now.”
It’s not guesswork — it’s evidence.
💪 ToothOps Takeaway
White doesn’t always mean “drill.”Color is only one clue — and not even the most important one.
Modern dentistry puts biology before drilling, meaning we prioritize prevention, remineralization, and risk reduction before picking up a bur.
Your smile deserves a dentist — and a dental student — who can read the whole story behind those tiny white spots.
@ToothOps | Fuel Your Smile 😊
Stay tuned for more insights and educational content in our blog.
Disclaimer: Content is for educational purposes only and not a substitute for medical or dental care.
© 2025 ToothOps | All Rights Reserved