
🦷 Why Local Anesthesia Fails in Inflamed Teeth
 ToothOps3 min read
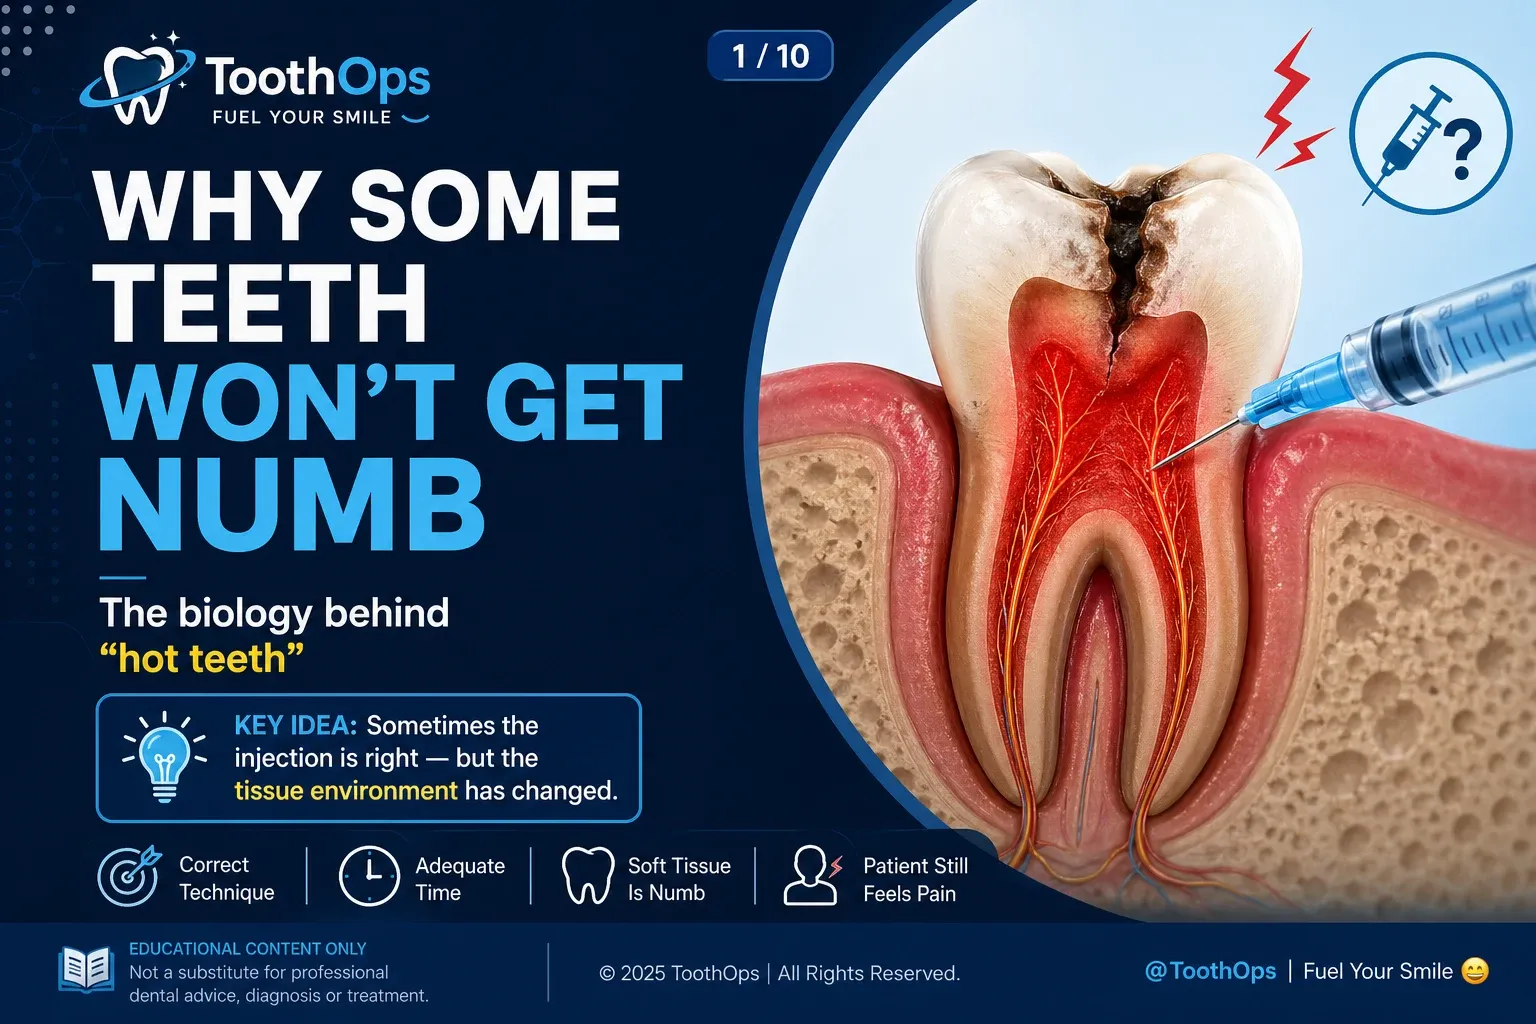
Understanding the Biology Behind “Hot Teeth”
🔍 Introduction
Few moments in clinical dentistry are more frustrating than when local anesthesia appears to fail.
- The injection is placed correctly
- The technique is sound
- Adequate time is given
Yet the patient continues to feel pain.
At first, this is often interpreted as a technical problem.
In many cases, however, the issue is not technical.
👉 It is biological.
🧠 The Problem of Assumption
Local anesthesia is often approached as a simple procedural step:
- deliver the drug
- wait for onset
- proceed with treatment
This assumes that drug delivery alone determines success.
In reality, anesthetic effectiveness depends on:
- local tissue environment
- physiologic state of the nerve
When these are altered, even correct technique may not produce the expected outcome.
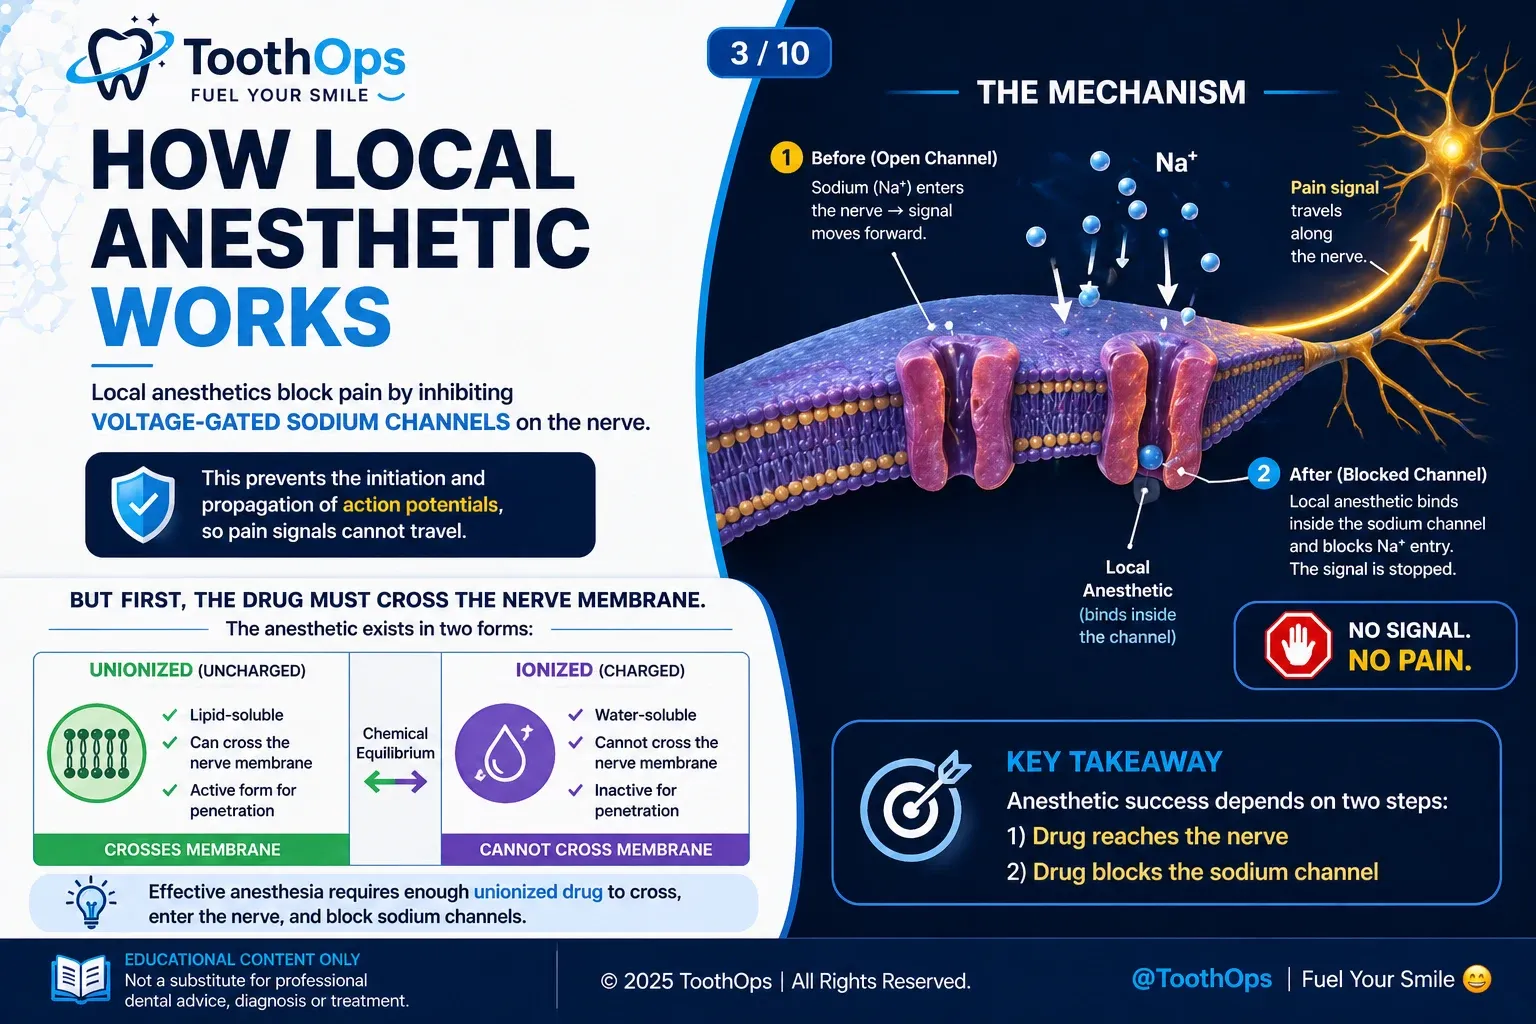
⚙️ Pharmacologic Principles in Context
Local anesthetics block pain by:
👉 inhibiting voltage-gated sodium channels→ preventing propagation of action potentials
For this to occur, the drug must cross the nerve membrane.
This depends on a chemical equilibrium:
| Form | Property | Function |
|---|---|---|
| Unionized (uncharged) | Lipid-soluble | Crosses nerve membrane |
| Ionized (charged) | Water-soluble | Cannot cross membrane |
👉 Effective anesthesia requires sufficient unionized drug.
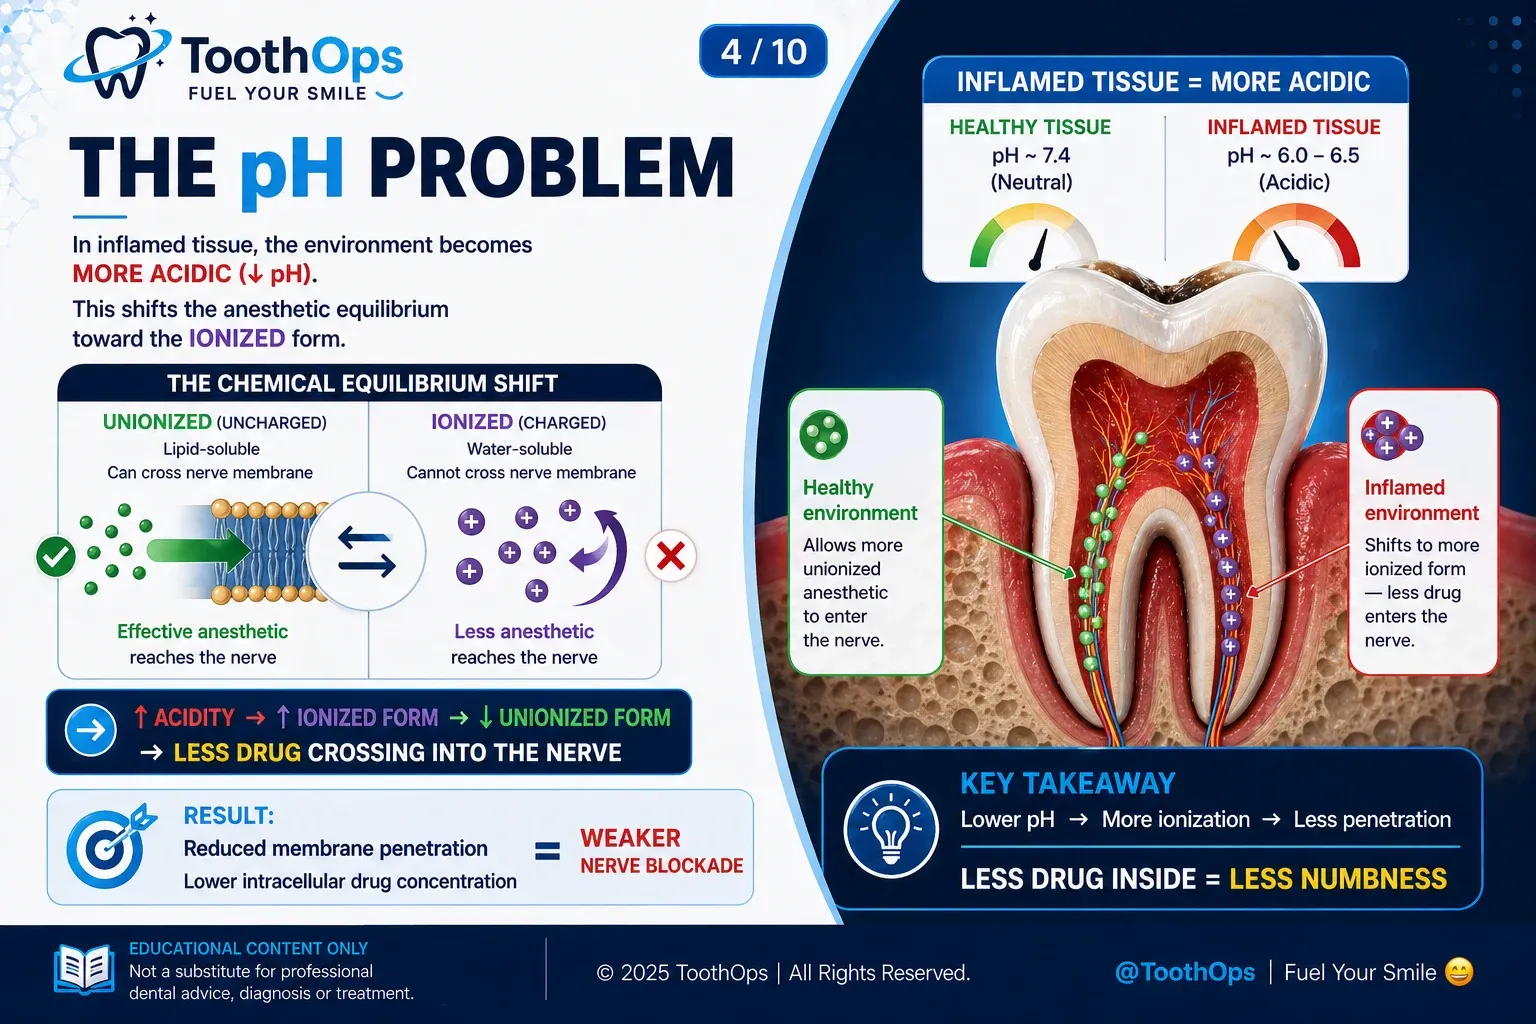
🔬 What Changes in Inflamed Tissue
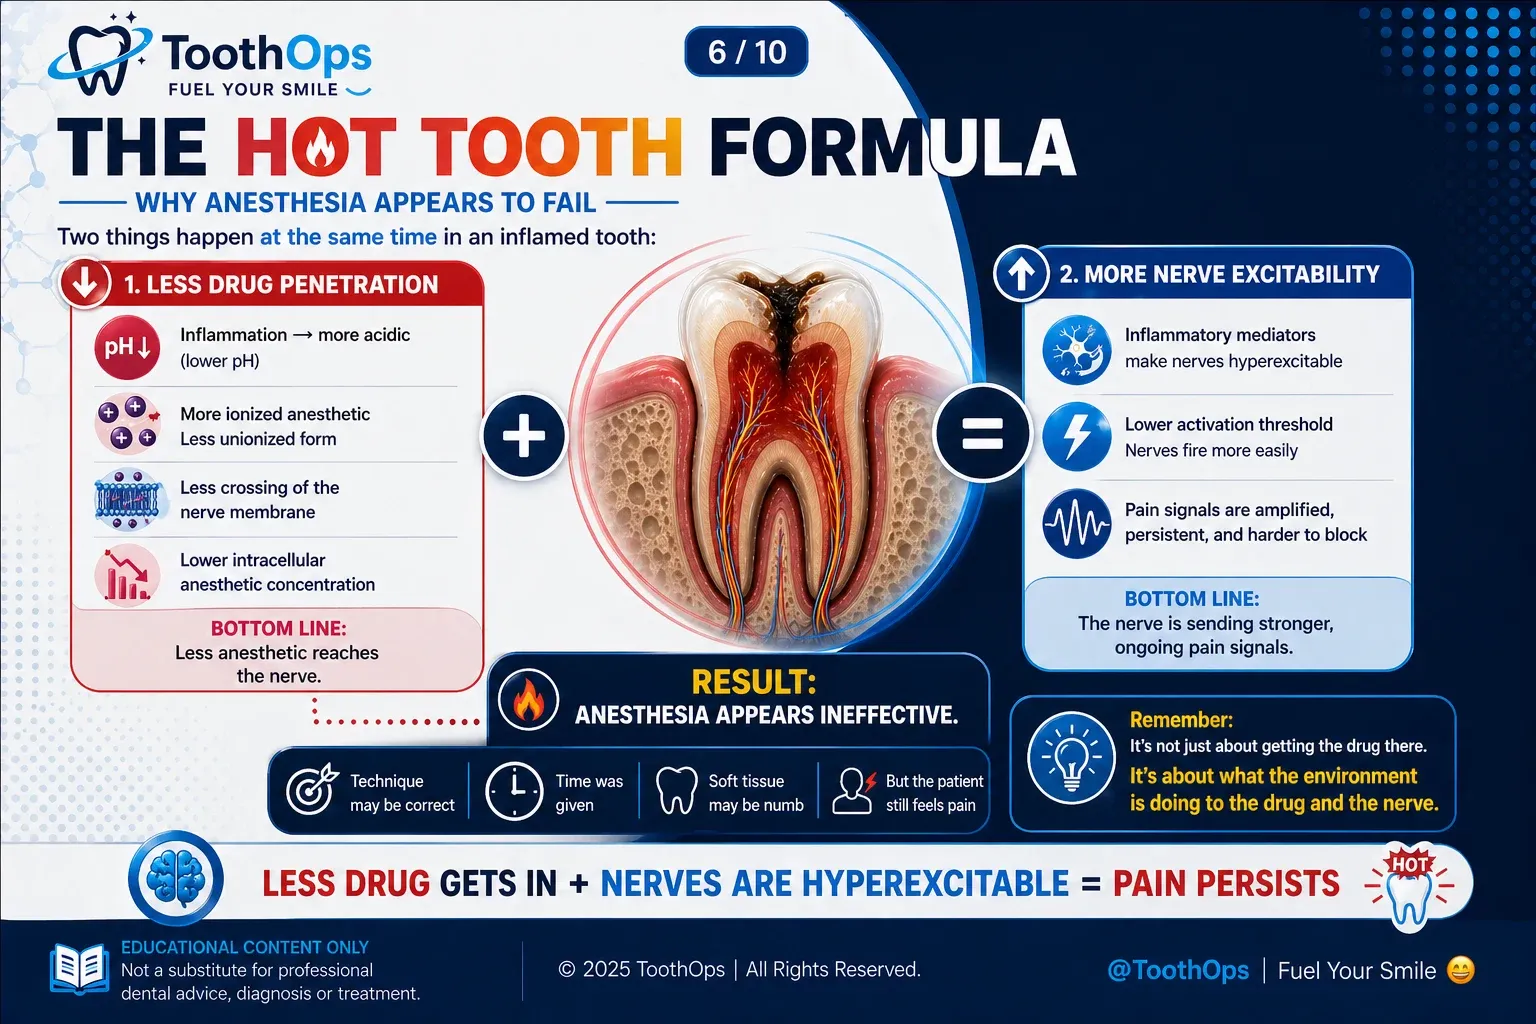
Inflamed tissue becomes more acidic (↓ pH).
This shifts the equilibrium:
- ↑ ionized form
- ↓ unionized form
👉 Result:
- reduced membrane penetration
- decreased intracellular drug concentration
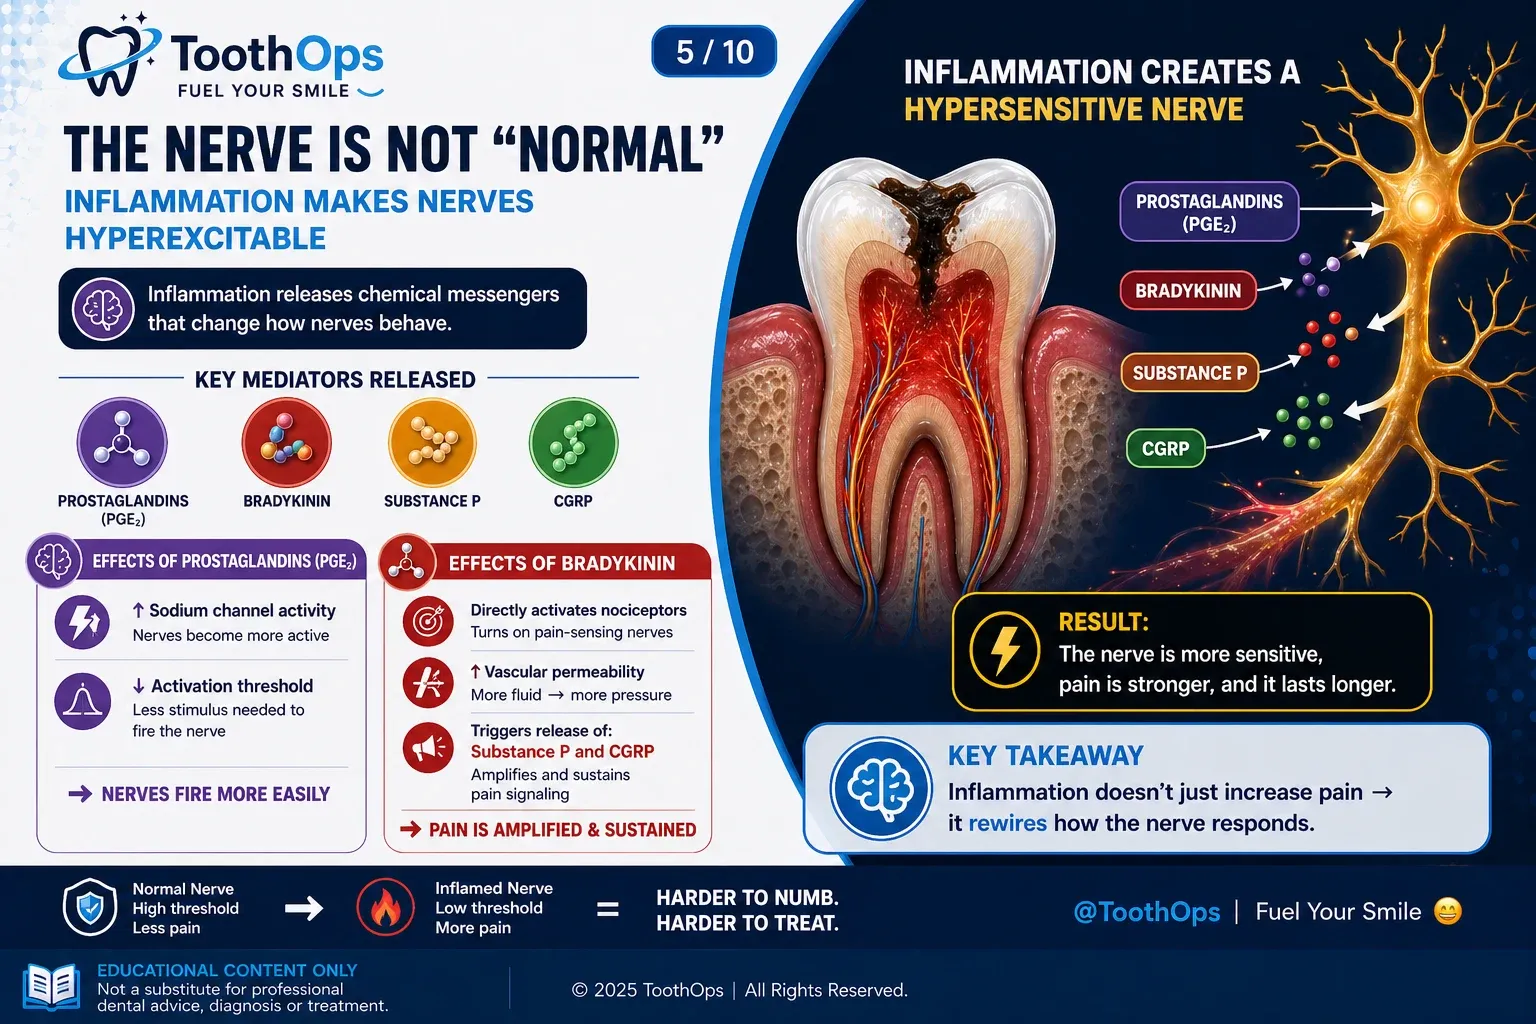
🧠 Neural Sensitization (Why Pain Feels Worse)
At the same time, inflammation alters nerve behavior.
Key mediators released:
- Prostaglandins (PGE₂)
- Bradykinin
🔬 Effects of these mediators:
Prostaglandins:
- ↑ sodium channel activity
- ↓ activation threshold
👉 nerves fire more easily
Bradykinin:
- directly activates nociceptors
- ↑ vascular permeability
- triggers release of:
- substance P
- CGRP
👉 amplifies and sustains pain signaling
🔗 The Combined Effect (Critical Concept)
Two changes occur simultaneously:
| Factor | Effect |
|---|---|
| ↓ Drug penetration | Less anesthetic reaches nerve |
| ↑ Nerve excitability | Stronger, persistent signaling |
👉 This explains why:
- anesthesia appears ineffective
- pain persists despite correct technique
🧩 Why Repeating the Same Injection Fails
Repeating the same injection does NOT change:
- tissue pH
- drug ionization balance
- nerve sensitization
👉 Result:
- more volume
- same limitation
This is why repeated injections without strategy change often lead to:
- patient discomfort
- clinical frustration
🧭 Clinical Implications
Management should shift from repetition → strategy:
Adjust delivery:
- intraosseous injection
- periodontal ligament (PDL) injection
Improve diffusion:
- consider articaine
Anticipate difficulty:
- “hot teeth”
- lingering or spontaneous pain
👉 These findings are not separate—they reflect the same inflammatory state.

💡 For Patients
Difficulty getting numb can feel concerning.
In inflamed teeth, this can be expected.
Helpful observations to share:
- Does the pain linger after stimulus?
- Does it happen on its own?
- Is it difficult to localize?
👉 These details help guide treatment decisions more effectively.
🧠 For Students and Clinicians
Anesthetic success depends on more than technique.
Evaluate:
- tissue pH
- drug ionization state
- nociceptor sensitivity
- inflammatory mediator activity
👉 Think in sequence:
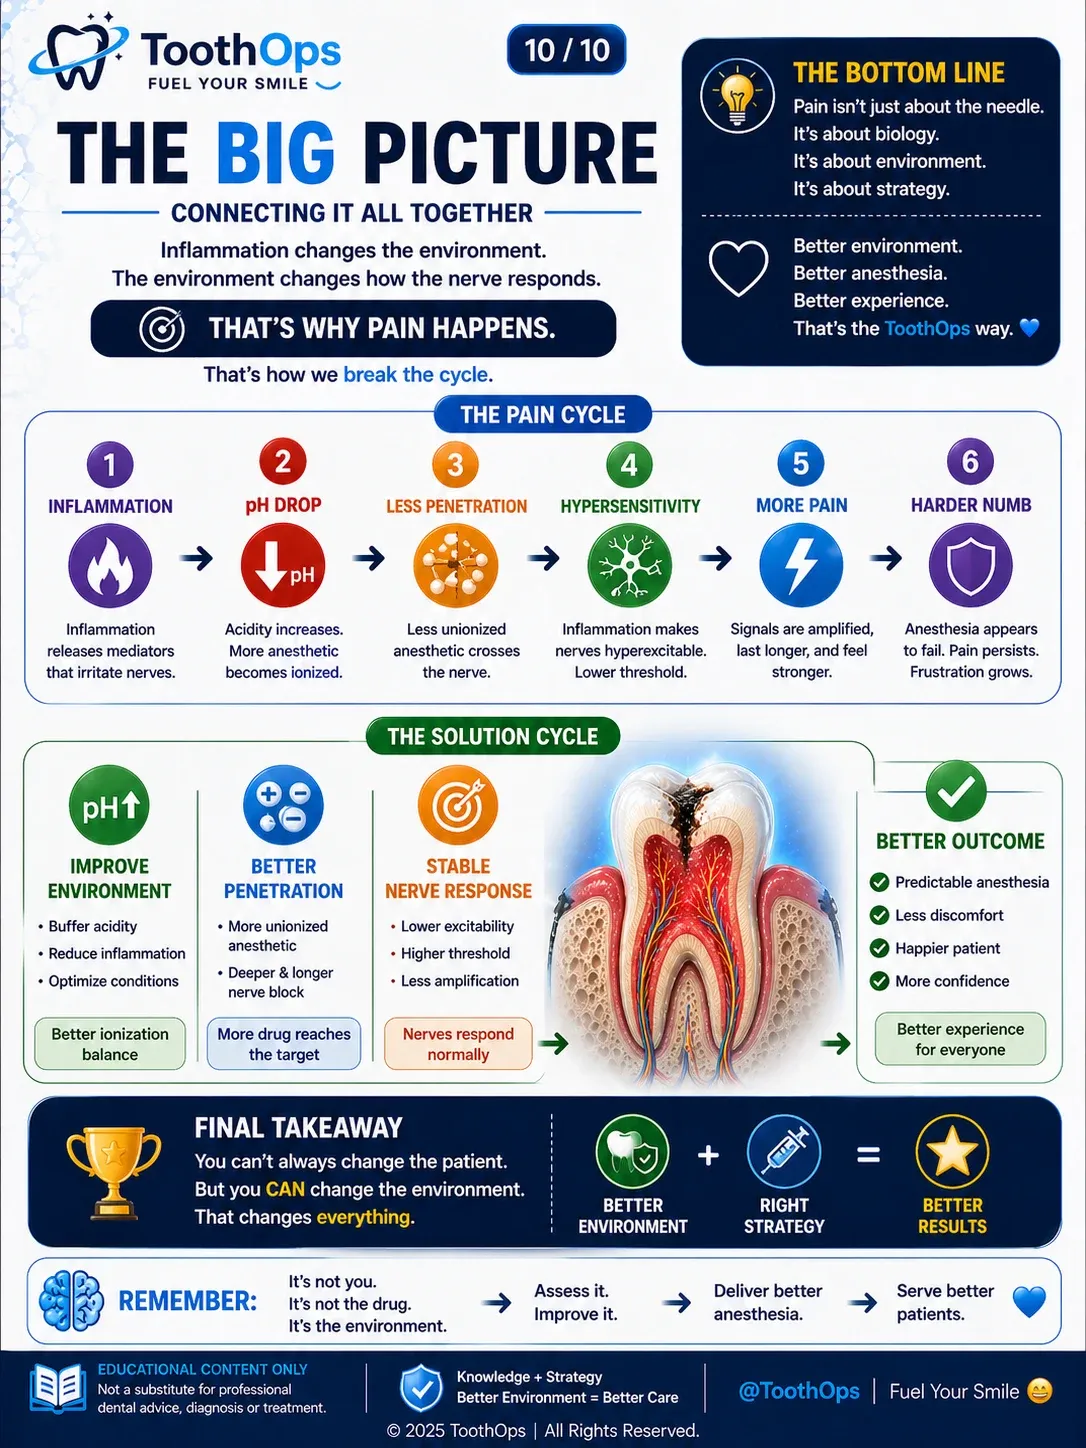
Environment → Drug behavior → Nerve response → Outcome
🏁 Final Thought
When anesthesia fails, the instinct is to question technique.
A more useful question is:
👉 What has changed in the biology of this tissue?
Understanding that shift transforms anesthesia from a procedure into a process of clinical reasoning.
@ToothOps | Fuel Your Smile 😊
Stay tuned for more insights and educational content in our blog.
Disclaimer: Content is for educational purposes only and not a substitute for medical or dental care.
© 2025 ToothOps | All Rights Reserved.